

[Updated 9/28/2026]
NOTE: This article is in the process of being updated to reflect new hospital data released by the Illinois Department of Public Health in early August 2026. Note that the listings for all hospitals for which data is available have been updated with the new data in our birth settings directory.
If you had a c-section with your previous pregnancy and are considering a “vaginal birth after cesarean” (VBAC) this time around, there’s a lot to consider.
This article offers a road map to help you navigate some of the important questions you may have, including:
- What are the best hospitals for VBAC in the Chicago area?
- Where can I have a midwife-attended VBAC?
- Do any midwife-led birth centers support VBAC?
- Where can I have a VBAC after more than one cesarean (VBA2+C)?
- What other hospitals have above-average VBAC rates?
- VBAC or repeat Cesarean? — resources to help you decide
- What else should I know about searching for a VBAC-friendly hospital and practitioner?
What are the best hospitals for VBAC in the Chicago Area?
If you are hoping to have a vaginal hospital birth after your prior cesarean birth, you’ll have your best chance of success if you choose a VBAC-friendly hospital. And the best indicator of a VBAC-friendly hospital is a high VBAC rate. Basically, the proof is in the pudding!
About the VBAC rates reported on BirthGuide
Providers are listed on BirthGuide as having a risk-adjusted VBAC rate that is “among the highest” if their VBAC rate is one standard deviation or more above the average rate for all hospitals listed on BirthGuide. (BirthGuide lists all maternity hospitals in Cook, Dupage, Kane, Lake, McHenry and Will counties that were included in the Illinois Department of Public Health’s “Illinois Health Report Card” as of 8/1/2026.) On the mobile version of the site, these providers’ VBAC rates are listed as “high”.
The VBAC rates used in this calculation come from the Illinois Department of Public Health (IDPH), which reports the VBAC rates for all Illinois hospitals. The IDPH VBAC rates reflect the number of women who have had at least one prior c-section in the past and who then have a vaginal birth at that hospital in the reporting year, divided by the number of all women who gave birth at that hospital in that year who have had at least one prior c-section. So the VBAC rate takes into account both the women who try for a VBAC and the women with a history of c-section who schedule a repeat cesarean with this pregnancy. The VBAC rates reported by IDPH are risk-adjusted.
Some providers also self-report their VBAC success rate. The VBAC success rate is the percentage of all women who choose a trial of labor who ultimately have a vaginal birth. That rate will be much higher than the overall VBAC rate because it considers only the population of women who qualify for and elect to try for VBAC, without taking into account women who are scheduled for a repeat c-section.
The highest overall VBAC rates will reflect both that a high percentage of women are offered a trial of labor and that skilled support helps a high percentage of those to succeed.
Based on most recent Illinois Department of Public Health statistics (covering the period 10/1/2024 to 9/30/2025), here are the six hospitals with the highest VBAC rates in the Chicago area. (These are the hospitals with uncomplicated VBAC rates at least one standard deviation above the average for Chicago-area hospitals.)
| Hospital | Risk-adjusted VBAC rate | # of uncomplicated VBACs | # of births to women/people with a prior C-section |
| Loyola MacNeal Hospital | 43.3 | 42 | 97 |
| Roseland Hospital | 42.9 | 9 | 21 |
| Endeavor Health Evanston Hospital | 38.6 | 184 | 477 |
| Advocate Trinity Hospital | 35.9 | 28 | 78 |
| Endeavor Health Swedish Hospital | 34.3 | 119 | 347 |
| Endeavor Health Highland Park Hospital | 30.6 | 81 | 265 |
Where can I have a midwife-attended VBAC?
[insert text]
Where can I have a VBAC after more than one cesarean (VBA2+C)
The American College of Obstetricians and Gynecologists takes the position that VBAC can be a safe and appropriate choice for some women who have had two prior cesarean births. Not all providers offer the option of VBAC to women who have had more than one c-section, but several do — including a number of the hospitals with the highest VBAC rates. If you’ve had two cesarean deliveries before this pregnancy, you may still have the option of a vaginal birth this time around, depending on the reasons for your past c-sections and other factors.
You can search for these hospitals in the BirthGuide Chicago birth settings directory using the VBAC+2 search filter:
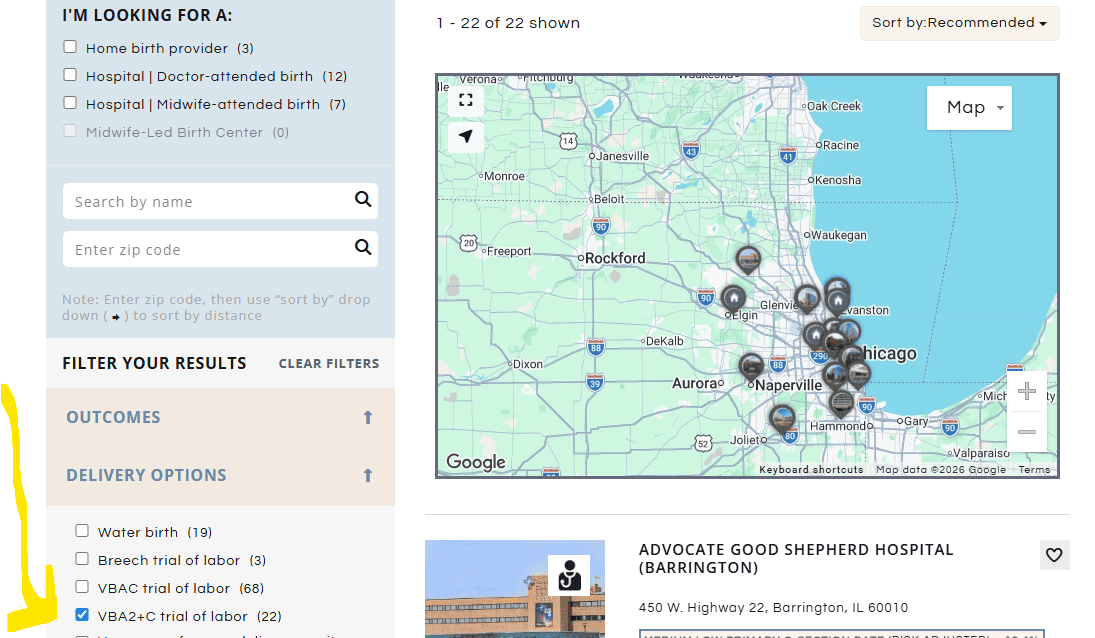
These will be good places to start if you’ve had multiple C-sections in the past and want to try for a VBAC with this pregnancy. Different providers will have different criteria for a trial of labor after two c-sections: just because one provider says no doesn’t necessarily mean they all will.
What other hospitals have above-average VBAC rates?
[insert table]
Do any midwife-led birth centers in the Chicago-area support VBAC?
There is currently only one midwife-led birth center in the Chicago area, which is The Birth Center at PCC
[Note that several Chicago-area home birth providers may offer the option of a home birth after cesarean, but most likely only if your most recent birth was a successful VBAC. This article focuses on options for those who have not had a vaginal birth since their last cesarean, so we don’t address the option of VBAC at home.]
VBAC or repeat Cesarean? — resources to help you decide
The old adage “once a cesarean, always a cesarean” has been debunked.

The American College of Obstetricians and Gynecologists (ACOG) current practice bulletin relating to VBAC takes the position that women with one or two previous c-sections are candidates for a “trial of labor after cesarean” (TOLAC) and should be counseled about and offered a TOLAC. (See “Summary of Recommendations and Conclusions” section in full text of Practice Bulletin.) ACOG also recognizes that “the ultimate decision to undergo TOLAC or a repeat cesarean delivery should be made by the patient in consultation with her obstetrician or obstetric care provider. The potential risks and benefits of both TOLAC and elective repeat cesarean delivery should be discussed.”
The American College of Nurse Midwives (ACNM) similarly encourages a trial of labor after c-section (TOLAC): “Pregnant people should receive evidence-based information and counseling to guide their decision-making when they consider labor after cesarean versus elective repeat cesarean. Shared decision-making should be based on patient preferences and the potential benefits and risks of VBAC, planned elective repeat cesarean, and cesarean during labor to pregnant people, newborns, and future pregnancies.” 2024-Care-of-the-Pregnant-Person-with-a-History-of-Cesarean-Birth.
So VBAC is an option every woman should at least look into.
Here are some resources to help you weigh trial of labor vs. planned cesarean:
- ACOG FAQs: Vaginal Birth After Cesarean Delivery – Deciding on a Trial of Labor After Cesarean Delivery – FAQs from the American College of Obstetricians and Gynecologists
- Childbirth Connection – offers a helpful overview of VBAC, including “VBAC Basics”, “Planning Ahead”, “Research and Evidence”, and “VBAC Resources”
- International Cesarean Awareness Network (ICAN) – a leading national organization dedicated to preventing unnecessary cesareans, supporting cesarean recovery and promoting vaginal birth after cesarean (VBAC)
- Lamaze International infographic – a one-page summary of facts about VBAC
- VBAC.com – a source for evidence-based information, resources, continuing education and support for VBAC
- VBAC Facts – offers a comprehensive paid online course for women and their partners that will walk you through the research and other considerations to help you decide whether you’re interested in VBAC
What else should I know about searching for a VBAC-friendly hospital and practitioner?
If you decide to try for a vaginal birth this time around, your first priority should be to find a supportive provider. You’re not just looking for someone who says “yes”, you’re looking for someone who enthusiastically supports a trial of labor after c-section.
This is the key piece of advice offered by Erica Fleischer, who at the time of this interview was leader of the Chicago Chapter of the International Cesarean Awareness Network, Inc. (ICAN) — a nonprofit organization whose mission is “to improve maternal-child health by reducing preventable cesareans through education, supporting cesarean recovery, and advocating for vaginal birth after cesarean (VBAC).”
As Fleischer explains, “You’ll hear from a lot of providers that, ‘Sure, you can have a VBAC.’ But then if you don’t go into labor spontaneously before 39 or 40 weeks, they want to do a repeat c-section. Or if you develop a medical condition that means you need to deliver right away, they refuse to induce you, so they’re basically requiring you to have a c-section. We always tell people that the most important thing is to have a provider is truly supportive.” That means providers who actively promote VBAC.
Dr. Richard K. Silver is an obstetrician and gynecologist specializing in maternal-fetal medicine at Endeavor Health Evanston Hospital, which is where Erica Fleischer had her VBAC and which has one of the very best VBAC rates in the Chicago area. Dr. Silver attributes the hospital’s excellent outcomes in part to the fact that it’s a Level III hospital, which means that the doctors and midwives there see some of the rare but serious complications that can arise when a woman has multiple cesareans.
As Dr. Silver explains it, “Repeat cesarean is more risky for the mother. For instance, we inherit patients from other hospital systems when their placenta grows through the uterine wall and threatens their life. We handle up to 20 cases a year. These are really challenging cases, involving transfusions, multiple surgeries, urological issues. This is one of the risks of repeat cesareans and one of the long term consequences of not offering vaginal trial of labor appropriately.”
 So what does it mean to offer trial of labor appropriately? Dr. Silver’s answer is that it starts with good counseling. “You have to be non-coercive, but you also have to overcome the understandable barrier. Someone’s had a less than ideal experience with their prior labor and it ended with c-section. If it were me, I’d raise my hand and say, ‘This time, let’s skip the labor and just repeat the cesarean.’ You can absolutely understand why they’d make that choice. So you have to address that with factual data, with good information, including the effect that a second cesarean section may have on the pregnancies after this one. Women need the data.”
The question of training is clearly important. Dr. Silver has been in practice for more than 30 years and he has seen drastic changes in approaches to VBAC over that time. “When I was in training, we offered pretty much everybody a trial of labor and the success rate was around 80%. For women with non-recurring indications [meaning that the reason for their previous c-section is not likely to recur this time around], 8 or 9 out of ten would delivery vaginally. And even those with the lowest odds of success, maybe someone who got stuck at seven centimeters or who pushed for four hours and still couldn’t deliver her baby, even those women have a 50/50 shot at delivering vaginally.”
Dr. Silver notes that confidence is critical. “When choosing a provider, I would ask, ‘what is the culture of your labor and delivery unit? Are your nurses and other folks supportive of this or do they get anxious when they have a patient with a scarred uterus?’” The anxiety of people around you can undermine your confidence and derail your labor.
Because it’s so important to find a supportive provider, don’t limit yourself to nearby hospitals. An hour or even an hour and a half drive might be inconvenient for prenatal visits and unpleasant when you’re in labor, but ultimately could be worth it.
As Dr. Silver points out, “People get anxious about being far from the hospital, but I think that’s a little overrated, especially with a VBAC. A lot of moms had a protracted first labor so they’re not likely to have a rapid labor this time around.” Dr. Silver has cared for vaginal trial of labor patients who live as much as an hour and a half away. That means you can look beyond the hospitals closest to you to find providers you really trust. In the list of top options for VBAC below, you’re likely to find a hospital well within a safe distance almost no matter where you live in the Chicago area.
Other factors to consider when choosing your provider
The most important thing is to find a provider who is supportive. But there are other considerations as well.
One is monitoring technology. If you’re trying for a vaginal birth after cesarean, you will likely be required to have continuous electronic fetal monitoring, where a belt around their belly transmits fetal heart tones to a receiver. In some hospitals, the monitor significantly limits the ability to move around. But some hospitals offer the option of monitoring by telemetry, which transmits the fetal heart tones wirelessly. That allows you to walk around instead of being tethered to the monitor. As Erica Fleischer puts it, “All Chicago area hospitals will require you to be monitored the whole time for a TOLAC [trial of labor after cesarean], but that doesn’t have to mean you’re stuck on your bed.” Being able to move around and try different positions can help you labor effectively, and an effective labor is less likely to end with a cesarean.
Another question to ask is whether there is an anesthesia team in the hospital at all times. This is important so that if a cesarean birth becomes necessary, it can be performed without delay.
 And Fleischer has a few more recommendations for those who want a VBAC. “First, hire a doula. The evidence shows that they reduce the rate of c-sections, and that kind of support is particularly valuable for VBAC. Second, if your c-section was for failure to progress or failure to descend, consider body work like physical therapy, chiropractic or the Spinning Babies technique. There are plenty of women who address physical issues that made their first labor difficult and then have no issue with their next birth. And third, work through any emotional trauma you may carry from your first labor. ICAN offers support for that, including through a closed Facebook group.”
Summing it up
 Although the evidence supports trial of labor for most women who’ve had cesarean births, not all providers are wholeheartedly comfortable with VBAC. If you’re considering a vaginal birth this time around, don’t stop at a discussion with your current provider. Instead, plan to get opinions from several doctors and/or midwives who support and have attended lots of successful VBACs. You’ll get a more balanced feel for the risks and benefits of a trial of labor by hearing multiple points of view, and you’re also more likely to find someone you truly connect with. A trusting relationship is especially important for a trial of labor after c-section since you need to feel confident that you and your provider have the same goals.
The best way to find VBAC-supportive providers is to start with hospitals and midwife-led birth centers that have high VBAC rates. Remember that not all hospitals and not all individual practitioners have the same criteria for trial of labor after cesarean. Just because you don’t qualify in one setting does not mean that you don’t qualify anywhere.
You can also find a list of BirthGuide members who can help you prepare for a VBAC here.
You don’t need to limit yourself to the hospitals closest to you. Many providers will agree to care for you even if you are traveling a distance to get to them. Given the importance of finding a supportive provider, cast a wide net if you need to.
When you’re interviewing providers at your setting of choice, here are some questions to ask:
- Will you allow me to go past my due date if that’s my informed decision?
- Are you willing to induce or augment my labor if that becomes medically necessary?
- Will I have fewer options in labor because I’ve had a previous c-section?
- What are the advantages and disadvantages of a trial of labor in my case?
- What are the advantages and disadvantages of planning a repeat cesarean in my case?
- How confident are you that I can successfully have a VBAC?
- Do you offer telemetric monitoring?
- Do you have anesthesia teams on-site 24/7?
The photos in this article document a successful VBAC and are used with the permission of Amanda E Photography in Peoria Illinois.